About Nesta
We are Nesta, the UK's innovation agency for social good. We design, test and scale solutions to society's biggest problems. Our three missions are to give every child a fair start, help people live healthy lives and create a sustainable future where the economy works for both people and the planet.
For over 20 years, we have worked to support, encourage and inspire innovation. We work in three roles: as an innovation partner working with frontline organisations to design and test new solutions, as a venture builder supporting new and early stage businesses and as a system shaper creating the conditions for innovation. Harnessing the rigour of science and the creativity of design, we work relentlessly to change millions of lives for the better.
Find out more at nesta.org.uk
If you'd like this publication in an alternative format such as Braille or large print please contact us at [email protected]
Authors
Adam Lang, Frances Bain, Grant Collinson
About this report
This report summarises insights gathered through a programme of stakeholder engagement work undertaken by Nesta Scotland and commissioned as part of the Health Foundation's independent inquiry into health inequalities in Scotland.
This work was designed and delivered by Nesta Scotland over two main phases of activity taking place between April and October 2022. This qualitative stakeholder engagement was supplemented by a quantitative survey carried out by the research agency, Diffley Partnership in October 2022.
The Nesta Scotland team spoke and engaged directly with more than 50 senior stakeholders working on issues relating to health inequalities from across Scotland covering statutory bodies, public agencies, local authorities, national bodies, large charities and smaller voluntary organisations.
A total of 210 stakeholders responded to the anonymous online stakeholder survey conducted by Diffley Partnership. These were drawn from a range of different stakeholder types, including charities, public and private sector organisations, academia and think tanks.
The findings captured in this report are a blend of anonymised quotes from participants, survey data as well as the summarised themes from workshops and interviews and recurring issues that arose across this project.
Given the nature of this work, the findings presented here are the product of a degree of interpretation by the Nesta Scotland team, synthesising what we heard from stakeholders collectively over the course of this activity.
The findings in this report represent summarised insights and should not to be taken as representative of the view of any one organisation or individual that engaged with this process.
Executive Summary
Nesta Scotland was commissioned by the Health Foundation in early 2022 to conduct a series of workshops and interviews with senior stakeholders from key organisations across Scotland working in and around issues relating to health inequalities. The aim of this work was to understand and collate views in relation to current health inequalities across the country. In particular, key issues such as the current drivers of health inequalities, barriers to action in addressing health inequalities and ideas for how we can do better in the future were all debated and discussed. The insight generated from this will feed into the Health Foundation's Health inequalities in Scotland: An independent review.
The findings from this engagement were supplemented by insight from the research agency Diffley Partnership, which conducted an anonymous online survey of stakeholders primarily in Scotland, but including some at a UK level too, in October 2022. The key findings from these combined strands of work are presented in this report.
It is important to note that this report does not represent the views or opinions of any one organisation or individual that engaged with this process. Instead, this paper presents summarised interpretations from the Nesta Scotland team based on what we captured throughout this engagement work.
What we heard clearly throughout this work was a sense of frustration from many stakeholders that health inequalities remain such a persistent and widespread issue in Scotland today, driven primarily by poverty and inequality. There was a strong desire, across sectors, to see more radical and bold action taken to tackle the root causes of poverty and better prevent health inequalities. There was a clear ambition for Scotland to focus more on longer-term and preventative outcomes when thinking about how we fund, design and resource public services, at all levels, as well as both national and local policies aimed at reducing health inequalities.
We heard concerns about how centralised and risk-averse the operating environment in Scotland can feel for those working in it and how this can impact negatively on trust between and across different institutions and sectors in the system. We heard that competing and growing demands often leave statutory bodies, public services and voluntary organisations in Scotland with little resource to design, deliver and invest in more preventative interventions. There was also a clear desire to improve how we share insights and learn from ourselves about what works and what doesn't in tackling health inequalities, as well as the need for more and better open data relating to health inequalities to facilitate this.
Despite the many challenges facing those working in and around health inequalities in Scotland, there are nonetheless reasons for optimism. There is a strong shared desire from those in the system for Scotland to do more on health inequalities and preventative action. We heard consistently that a gap exists between our rhetoric on health inequalities at a national level and the reality on the ground in our communities – Scotland's implementation challenge. However, all those we engaged with were keen to see this implementation gap tackled, which creates clear space and significant support for more ambitious action and innovation on health inequalities. The will to act is there across the system, but needs to be better enabled and empowered.
The Nesta Scotland team want to thank all those stakeholder organisations and individuals that engaged with this project and who gave so willingly of their time, wisdom and experience to inform this research.
"There is often a lack of willingness to take on board the idea that systemic change can take generations and this doesn't always align with short term decisions. System change takes time.”
- stakeholder participant
“We need to look at the systemic challenges for those folk at the margins who don't have the same opportunities for access to services or support. If you get it right for these groups, then you can get it right for the masses too.”
- stakeholder participant
Key findings from the stakeholder engagement
General views on the Health Foundation's Inquiry
- All stakeholders we engaged with welcomed the review and were keen to participate in the process and stay engaged.
- There was a strong sense from stakeholders that a lot is already known about the main issues driving health inequalities in Scotland. Also that the political, policy and operational landscape here already recognises and accepts the many wider social determinants of health inequalities.
- As such, there was strong encouragement for the Health Foundation's inquiry to articulate a bold ambition for action and better outcomes to help galvanise efforts across the system.
Current drivers of Scotland's health inequalities
- Persistent levels of poverty alongside growing income and wealth inequality across Scottish society were seen by stakeholders as the primary drivers of health inequalities in Scotland today.
- Multiple forms of insecurity and discrimination experienced by people in their day-to-day lives, such as insecurity of work, pay, housing, financial instability and access to food, also came up consistently as significant drivers for health inequalities
- Obesity and access to good quality food across the population was noted as a growing driver of health inequalities, particularly, but not exclusively, in rural and remote areas in Scotland.
Barriers to action on health inequalities in Scotland
- Many stakeholders noted Scotland's centralised and risk-averse operating environment as a barrier to taking new or radical approaches to tackle health inequalities.
- The challenges of Scotland's geography, demographics and varying population density across different local authority areas arose often as making it difficult both for standardising approaches and the effective scaling of proven interventions.
Scotland's implementation gap
- There was a consistent view that there is a gap in Scotland between our progressive political rhetoric or policy ambitions on health inequalities and what is actually enabled or resourced to happen on the ground.
- Stakeholders noted that there was no playbook for what good preventative action or good early intervention looks like on health inequalities in Scotland - which often led to ‘reinventing the wheel' when designing services or a lack of effective scaling of proven interventions.
- A consistent view from many was that our data generation and performance measurement systems in Scotland are not fit for purpose. This can limit our understanding and analysis of what works and what doesn't on tackling health inequalities and hampers preventative action. We are too often driven by counting simplistic output measures rather than properly assessing and analysing longer-term outcomes – and we often shy away from openly and constructively assessing what works and what doesn't.
How we can do better on health inequalities in Scotland
- The need to improve and better resource community planning, empowerment and enablement to help tackle health inequalities locally, arose regularly.
- Many stakeholders repeatedly stressed the need for longer-term, more joined-up and more coherent thinking in relation to both our policy development and service resourcing in Scotland. We heard regularly that progress is often hampered by short-term thinking and annualised funding models, at multiple levels, and too often reinventing the wheel when it comes to designing services.
- We heard strong views in favour of more radical models of wealth redistribution, such as a Minimum Income Guarantee (MIG), to help tackle our persistent levels of poverty and growing inequality.
How the Health Foundation inquiry can achieve impact
- There was a clear desire from many stakeholders to ensure that the Health Foundation's inquiry is bold in its language and ambition and acts as a rallying call for action and a renewed cross-sector focus on health inequalities.
- Many stakeholders noted the need for this inquiry to focus on a small number of ambitious actions to rally support across sectors and leave the detailed specifics around delivery to others. This view was tempered by some stakeholders that wanted to ensure that any actions or recommendations made by the inquiry are specifically attributed or assigned to ensure accountability for delivery.
"Our policies are generally fairly well conceived with the intention of trying to make a positive and progressive difference, but are often not resourced or thought through well in terms of delivery. We lack the spaces in Scotland for long-term thinking that joins up investment, planning and resource allocation.”
- stakeholder participant
Stakeholder survey findings
To supplement the qualitative engagement undertaken by Nesta Scotland, a short online survey of stakeholders was conducted by the research agency, Diffley Partnership. The aims of the survey were to engage the views of a wider group of stakeholders from across Scotland and the UK and to gather additional evidence on the issues surrounding health inequalities in Scotland. A total of 210 stakeholders responded to the online survey, drawn from a range of different stakeholder types, including charities, public and private sector organisations, academia and think tanks.
This section of the report summarises the findings from this survey work and is grouped into three main thematic areas:
- Drivers of health inequalities in Scotland
- Scotland's implementation challenge
- Barriers to action on health inequalities in Scotland
Drivers of health inequalities in Scotland
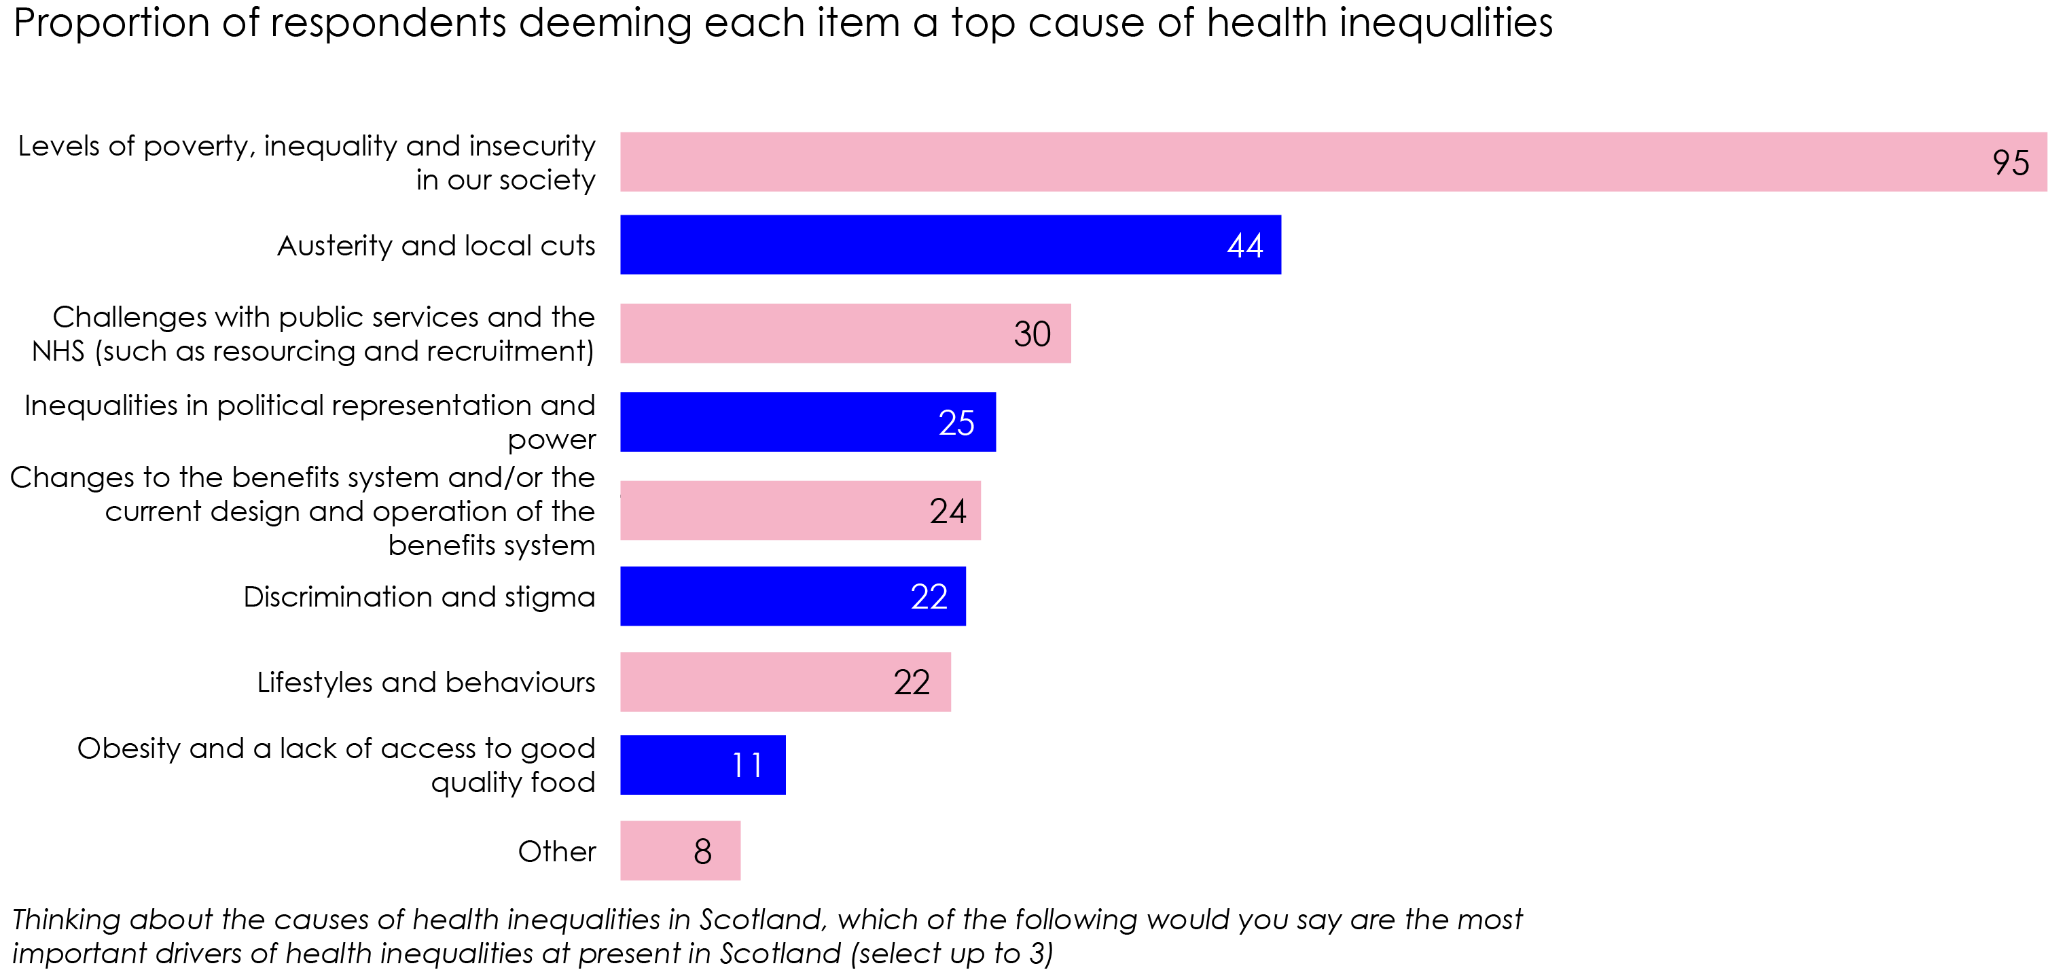
Poverty is seen by stakeholders to be the most significant driver of health inequalities in Scotland.
When asked to name the three issues which most contribute to health inequalities in Scotland, the overwhelming majority of stakeholders (95%) mention “levels of poverty, inequality and insecurity in our society” (Chart 1).
Perceptions of poverty as a major cause of health inequality far outweighed any other issue, with “austerity and local cuts” being mentioned by 44% and challenges with public services by 30%.
Scotland's implementation gap
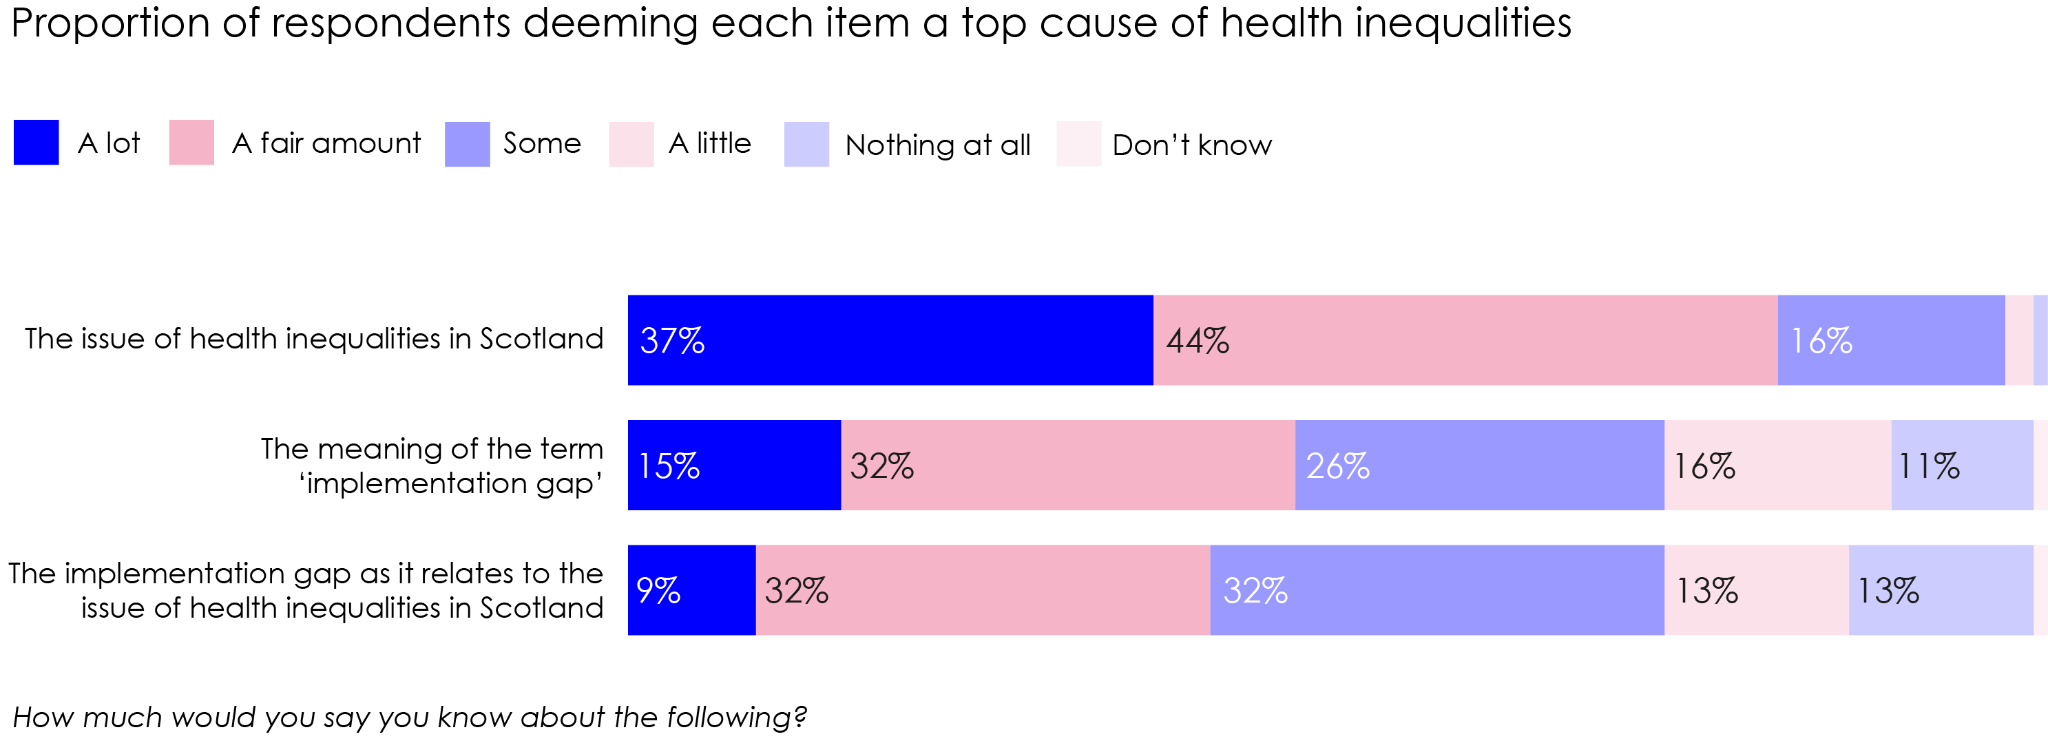
Nearly half of survey respondents reported knowing “a lot” or “a fair amount" about the implementation gap with only 1 in 10 saying they knew nothing about its meaning. In addition, just under three quarters (73%) reported knowing at least something about the gap as it relates to health inequalities in Scotland (Chart 2).
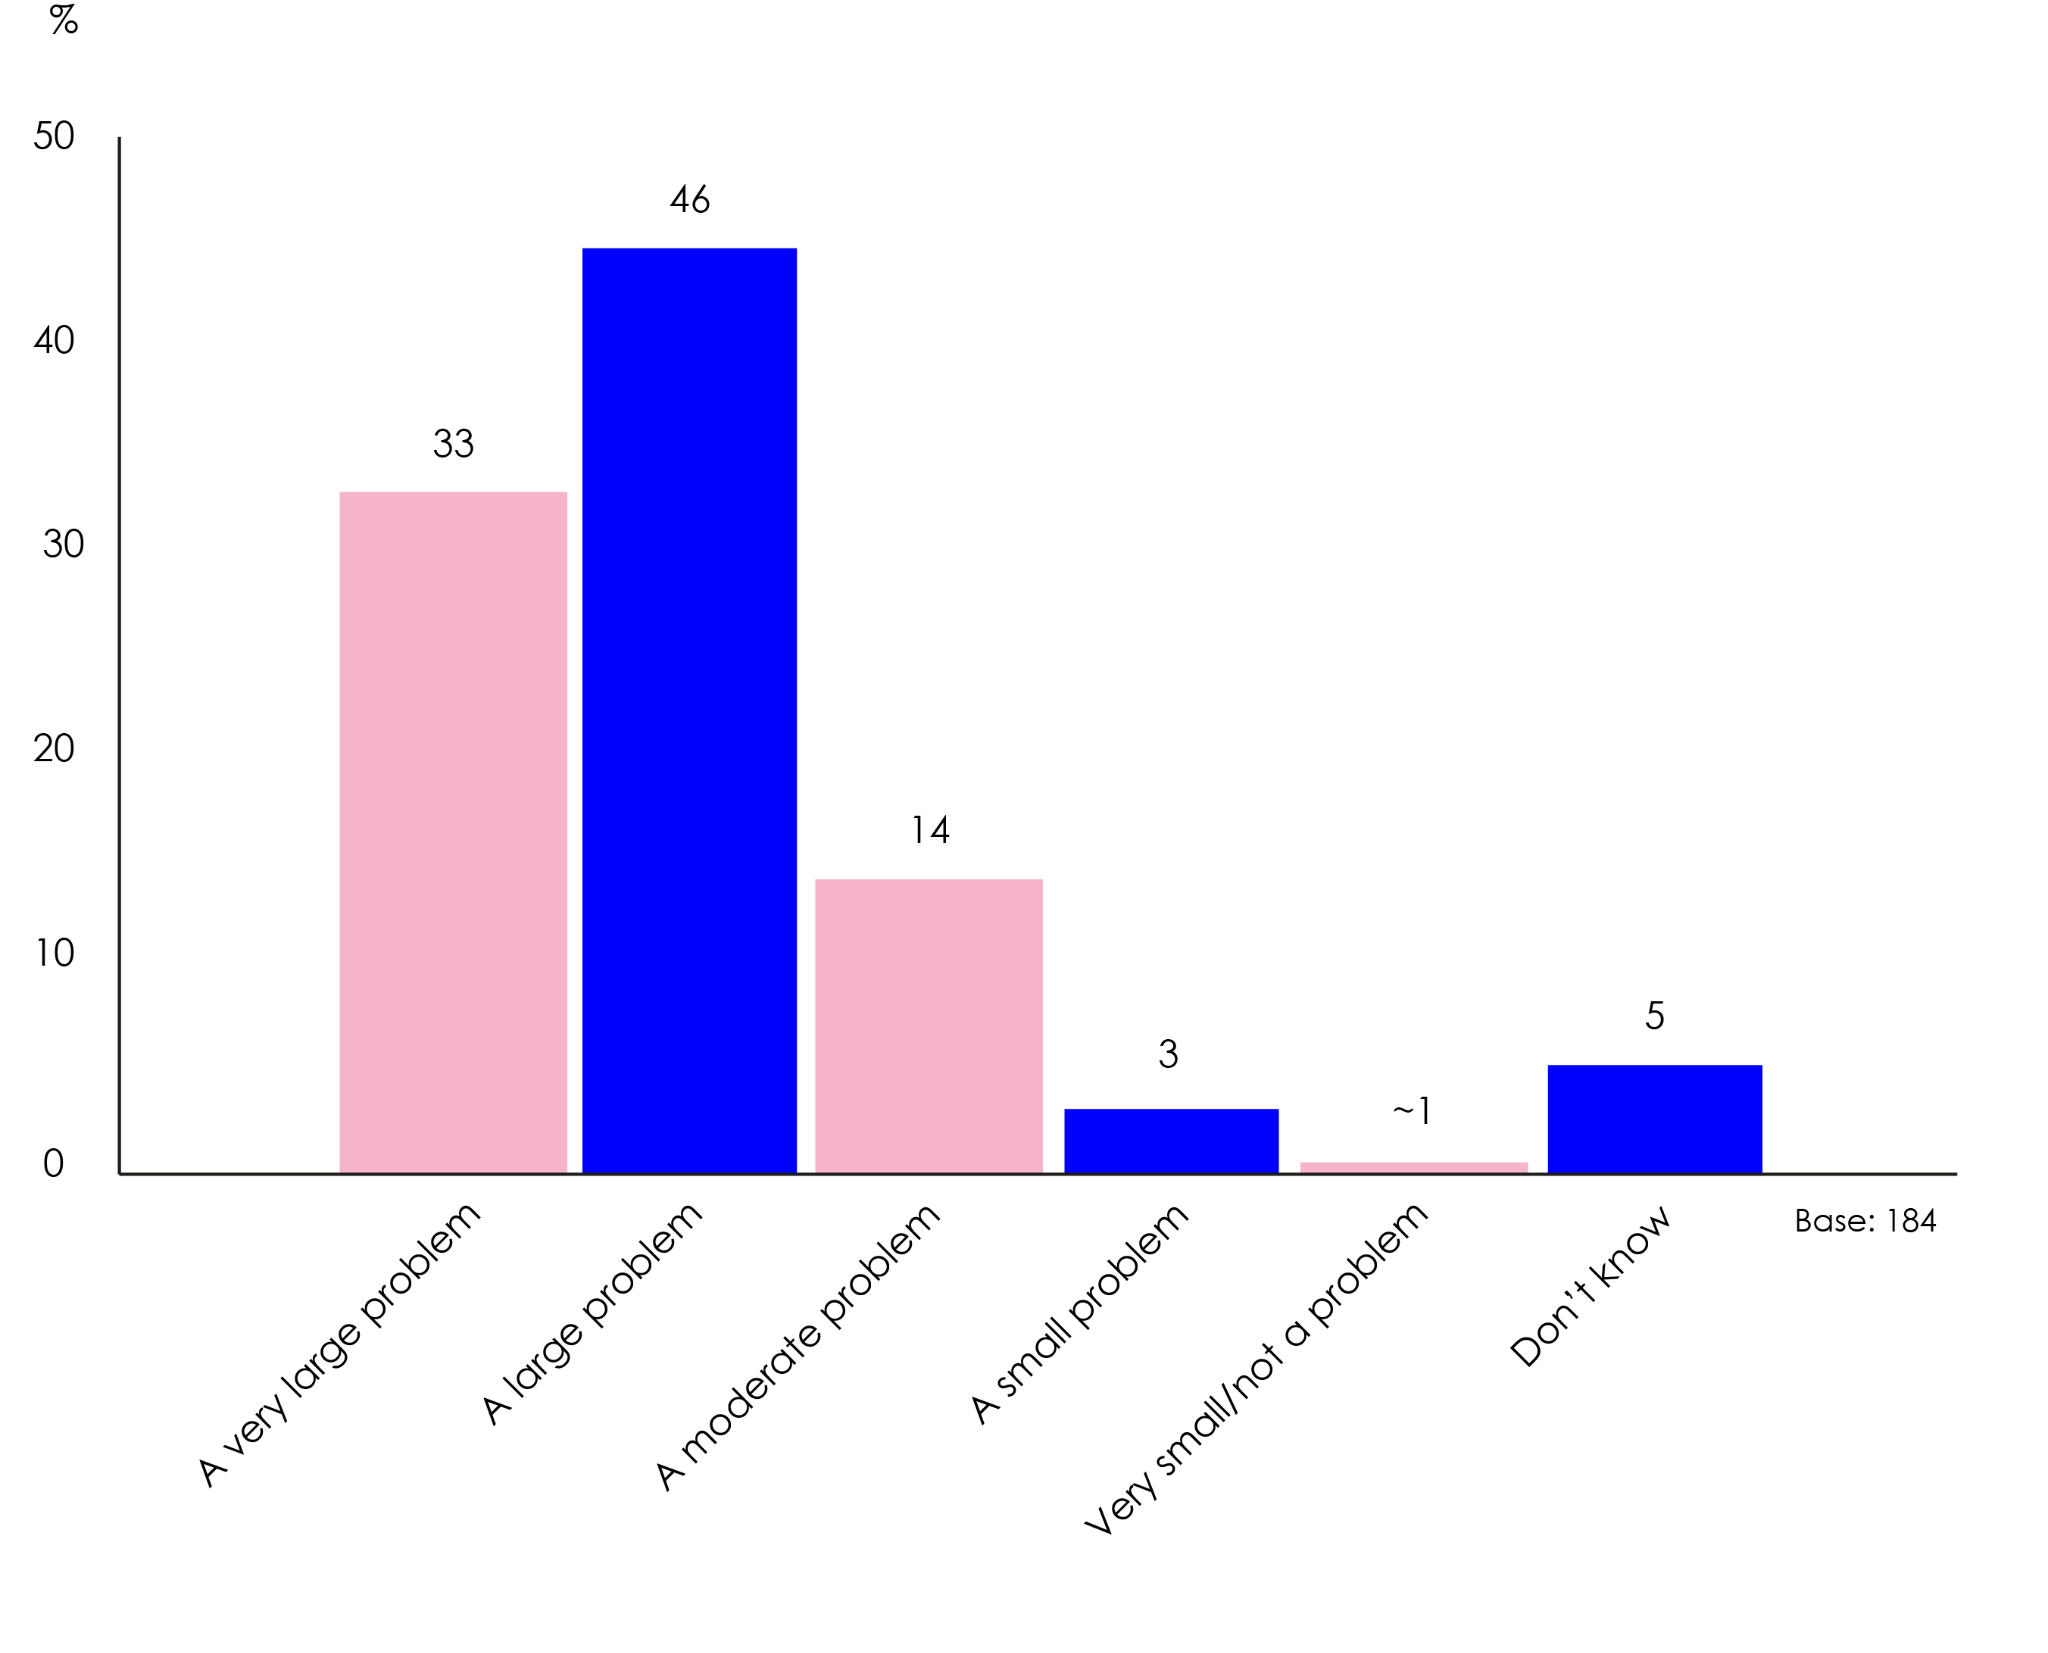
Almost 8 in 10 respondents (79%) considered the implementation gap to be a large or very large problem in relation to health inequalities in Scotland while only 3% considered it a small problem (Table 3).
Barriers to action on health inequalities in Scotland
The stakeholder survey highlighted many of the same barriers covered in the direct qualitative engagement work. When asked for the three main barriers to making progress on health inequalities in Scotland, the two most mentioned reasons were insufficient resourcing, funding and investment (which 47% put in the top three) and a lack of joined-up strategic thinking (mentioned by 46%) (Table 2).
| Base: 184 |
% |
| Insufficient resourcing, funding and investment |
47 |
| A lack of long-term and joined-up strategic thinking/planning |
46 |
| Short-termism in politics and consequent risk-aversion |
30 |
| Inconsistent funding streams to services and communities |
26 |
| An overly centralised approach to decision-making, planning and delivery, and/or insufficient community empowerment in this process |
23 |
| A lack of political will to reduce health inequalities in Scotland |
18 |
| Insufficient use of evidence and data in decision-making, and/or a lack of evidence/data on what works |
16 |
| Insufficient partnership working between different sectors |
15 |
| The difficulty of achieving sustained behavioural change |
14 |
| A lack of trust between different actors in policy and service design and delivery (e.g. central government, local government, and the voluntary sector) |
13 |
| Insufficient inclusion of frontline practitioners in service-design and planning |
11 |
| An inability/unwillingness to trial new approaches in service-delivery |
7 |
| A lack of ideas around how to tackle health inequalities in Scotland |
5 |
| Excessive monitoring and data-collection |
4 |
| Something else (please specify) |
15 |
General themes from initial engagement
The following is a fuller summary and synthesis of the key issues identified by stakeholders who attended Nesta Scotland's initial phase of workshops in the Spring of 2022.
All participants we engaged with welcomed the Health Foundation's independent inquiry. There was broad support for more independent voices in this space that are not afraid to constructively critique existing systems. Stakeholders were keen to ensure that the inquiry was aware of other complementary and important work in this area in Scotland, such as the Scottish Parliament's Health and Sport Committee inquiry into health inequalities, as well as the work of other notable organisations such as the Glasgow Centre for Population Health.
There was a strong sense from stakeholders that many organisations and agencies working in Scotland already know what the issues driving health inequalities are. And that the broader social determinants of health inequalities such as poverty, poor housing, poor public transport connectivity and limited active travel infrastructure, is widely acknowledged by those working in the political, policy and operational landscape.
As such, there was a consistent view that to add useful value to the landscape, the Health Foundation's work should not just review historical drivers of health inequalities but should also look ahead to how we tackle health inequalities in the future.
We also heard that the review should acknowledge the importance of Scotland's specific geographical challenges and significantly varying levels of population density in designing and delivering both effective policy interventions and standardised universal service models.
In almost every session facilitated by the Nesta Scotland team, there was a clear and consistent desire to ensure that this inquiry recognises that issues relating to health inequalities are systemic, often deeply socially ingrained and cyclical and that creating positive change takes time beyond any one political cycle. We heard regularly that there are no quick fixes, but that change is possible if supported, invested in and enabled over time.
“The term 'postcode lottery' is one of the worst phrases in policy. Universality is not good, the same for everyone does not work. Communities need power to address their own unique issues. The idea that equality equals uniformity pervades, but it is simply not true.”
- stakeholder participant
Underlying causes of health inequalities in Scotland
There was general acknowledgement that the issue of health inequalities is a complex and multifaceted problem in Scotland. However, there was a strong view from stakeholders that the issue is rooted in persistent and growing levels of poverty as well as income and wealth inequality across Scotland.
It was regularly noted by stakeholders that multiple forms of insecurity in people's day-to-day lives such as insecure work, pay, housing, personal finances or access to food played a significant role in driving and sustaining current levels of health inequalities. Several stakeholders highlighted that the state provisions in place to support people in poverty or living insecurely, such as Universal Credit, are insufficient to meet the basic needs of individuals and families and can too often trap people in poverty rather than helping them escape it.
Several stakeholders identified that multiple forms of discrimination in our society result in unequal access to services and support for minoritised groups or vulnerable individuals. This is exacerbated by the fact that many services are predominantly focused on crisis mitigation, rather than prevention or early intervention, and are too often not resourced adequately or in the right way to achieve more preventative outcomes.
Improving community empowerment was a strong ask from stakeholders to help local services or agencies tackling and responding to health inequalities in communities. We heard often that Scotland is becoming increasingly centralised in terms of resource allocation and authority to act.
We also heard that obesity and access to good quality food across the population is a growing driver of health inequalities, particularly in many rural and remote areas across Scotland.
A number of contributing factors to Scotland's health inequalities were identified by stakeholders over the course of our engagement work and can be broadly grouped under the following three broad headings:
Cultural and policy issues:
- At a population level, Scotland's historic and current cultural relationship with unhealthy food, alcohol and drug misuse.
- Risk aversion in our systems and politics (local and national) limits the appetite for bold and disruptive reform focused on prevention.
- Mistrust of the state and services among certain individuals and groups that can lead to a lack of engagement with services or support.
- Not always being evidence-led in our policy making, with ideology or personal belief from decision makers holding greater sway than robust evidence.
Structural issues:
- Multi-generational, cyclical poverty and unequal economic opportunities.
- Disjointed and uncoordinated approach to funding and resourcing of work to tackle health inequalities.
- The unequal provision within our built environment of essential infrastructure such as public transport and active travel facilities.
- Digital poverty and unequal access to services and trusted information online.
Operational issues:
- Short-term funding for key services and short-term thinking in our local and national policy focus on complex issues.
- Not enough robust analysis of what has worked in the past and why to support better scaling or replication of outcomes.
- Limited discretionary powers and resources for local authorities in Scotland means they are often seen as simply vehicles for statutory service delivery, rather than empowered local problem solvers.
While it was acknowledged that many of these issues overlap and are interconnected, it was these broad themes that came up most regularly from stakeholders across our initial sessions.
Barriers to action
As part of the workshops and interview sessions, we undertook exercises and discussions to better understand the views of stakeholders about the current barriers to action on health inequalities in Scotland.
Risk aversion
The Nesta Scotland team regularly heard concerns about Scotland's risk-averse culture for taking radical or new approaches to solve or address problems. This was often described as a fear of failure and was closely linked to, and associated with, our centralised political and operational landscapes, at both a local and national level, an often hostile media environment and our current approach to commissioning and procuring services across the public sector.
There was a consistent and strong message from almost all stakeholders that we do not do enough to empower and enable communities in Scotland. This was often linked to a concern that despite good rhetoric on supporting communities, it is rarely followed through with meaningful funding, resources or powers to act independently at a local level.
In addition, there was a sense from many stakeholders that Scotland has a fairly cluttered landscape of institutions and structures working on health inequality issues that are invested in the status quo of service delivery and as such would be strongly resistant to change or significant structural reform.
Many stakeholders expressed frustration that the prevailing process at a national level of consulting on legislation, passing a bill and then publishing an action plan fell short of the kind of sustained partnership approach, resourcing and local engagement and empowerment needed to drive the scale and pace of change required to meaningfully tackle Scotland's health inequalities.
We also heard regularly about the challenge of ensuring the Scottish public are brought on side with some of the potentially more ambitious or radical approaches needed to tackle health inequalities, such as the idea of a minimum income guarantee or the shift to investment in more preventative models of health, care or criminal justice.
“Adversarial party politics is a huge problem. We can't have our leaders in constant conflict. Even if we devolve power, if it is still adversarial it won't work."
- stakeholder participant
Adversarial politics and no safe space to fail
The adversarial nature of politics in Scotland which sees parties, politicians and, at times, the media automatically take opposing stances on issues and limited interest in working cooperatively across party lines was noted by stakeholders as a barrier to meaningful change or experimentation in service design and delivery.
There was a recurring view from many stakeholders that too often debate on progress or change in Scotland on complex social issues can quickly become mixed up in the wider constitutional discussion and therefore limits willingness to think or act radically to tackle health inequalities. This was often linked to the idea of having no safe spaces to test or fail in designing different service approaches or trialling new preventative delivery models.
There was a concern from some stakeholders that health inequalities can be seen, both by those in power and the public, as too hard or too complex a set of issues to tackle and that in Scotland we, as a society, have come to accept current high levels of inequality as normal.
Many stakeholders acknowledged that Scotland is not as good as it could or should be at reflective practice in policy or service delivery. It was noted on several occasions that we often do not know enough about specifically how and why a policy or service model has or hasn't worked in the past and this can lead to struggling to know what aspects to scale or replicate to increase impact. This view from stakeholders was recurring and fed into more detailed discussion on Scotland's implementation challenge detailed below.
"We can cite good examples of successes but they come despite the system and rely on strong, passionate individuals."
- stakeholder participant
“We need to recognise the pace and scale of change required and acknowledge that it is not just policy change, but cultural change that is needed in the way we think about these issues.”
- stakeholder participant
Scotland's implementation challenge
Further to our initial engagement with stakeholders in the Spring, Nesta Scotland held two further workshop sessions exploring the concept of Scotland's implementation gap in August and September. These workshops were supplemented by additional questions in the many one-to-one interviews conducted to specifically dig into issues around our implementation gap.
What does the implementation gap mean to stakeholders?
All stakeholders we spoke to recognised and accepted that there was a significant gap in Scotland between our ambitions and our actions on health inequalities. The most consistent view from stakeholders was that the implementation gap was best described as:
The gap between the intended result in policy and the actual result in practice.
Many of the stakeholders we spoke to felt frustrated and exasperated by the continued existence of an implementation gap around health inequalities in Scotland, despite many years working to make things better.
“Our implementation gap is a consequence of our failed systems and structures."
- stakeholder participant
Short-term thinking and our implementation challenge
Stakeholders felt the implementation gap was often a consequence of under-resourced services. However, it is important to note that what we heard was that this was not simply just about the amount of money that is available for different initiatives or services. Rather it is as much about the often short-term or transactional nature of funding that is available and the lack of long-term consideration for how we best use the resources and assets that we have to achieve sustainable impact.
The short-termism in Scottish politics and policy development came up regularly in this regard in all strands of engagement with stakeholders. Many expressed continued frustration at the way policy is often hastily conceptualised or designed and then passed to others to implement with not enough consideration given to adequate resourcing or clarity on delivery models and mechanisms.
Several stakeholders noted that in many important policy areas, there is a lack of coherence across portfolios, operating structures and finance, which compounds the implementation challenge.
Successive failure to shift resources away from acute need to early intervention or preventative measures was also regularly cited as a driver of the implementation gap for those working on health inequalities.
The issue of a perceived lack of trust at times between national and local government, and between parts of the public sector and the voluntary sector came up regularly as factor contributing to Scotland's implementation gap.
"We have the National Performance Framework, but we don't use it well enough. We should use this more proactively to inform and drive decision making and resourcing across existing silos or organisational structures.
- stakeholder participant
Better data
Many stakeholders brought up data on health inequalities in Scotland and at times opinions on this were divided.
There was a consistent view that we do not use data well enough in Scotland. Some stakeholders felt we were recording too many things and that we didn't always know what to do with the data or how to make best use of it. At the same time, others felt that we lacked regular, useful and actionable data-driven insight to inform both policy making and service design and delivery in a useful way.
Many stakeholders noted the need for more independent voices to produce, analyse and make widely available data in relation to health inequalities in Scotland. A recurring theme was that Scotland doesn't have enough think tanks or similar organisations that are fully independent of both local and national government that can constructively analyse and challenge existing assumptions and decision making.
“We are not as good as we could or should be at monitoring, collecting or analysing data and certainly not good enough at acting on it.”
- stakeholder participant
Ideas to address the implementation gap
Although responses and contributions on how to tackle the implementation gap were wide ranging, there are three main areas where responses to this question clustered together:
- The need for longer-term thinking: A clear and consistent theme across all our engagement was the need for decision makers and public financing to take a longer-term approach to policy making and service resourcing in Scotland. And to recognise the fact that many of these issues are complex and take time to see significant improvements.
- Get better at learning from ourselves: Another recurring theme was the need for Scotland to adopt an improved culture of learning from ourselves, sharing what works and being open and more self-critical in understanding what doesn't.
- A more radical ambition: We regularly heard that Scotland needs to be much more radical on health inequalities. The need for bolder action, more relational and preventative services and the need to pool resources and share accountability through joined-up working were recurring themes.
“Non-recurring funding for services is a waste of money in the context of tackling long-standing and deep rooted health inequalities. But it is still so common."
- stakeholder participant
"The difference between our national policy intent and local policy priorities can be significant. The National Care Service proposal is a good example of this -there is a big difference between local and national agendas in this regard.”
- stakeholder participant
Conclusions and observations
This work represented a unique opportunity to engage with a range of stakeholders in Scotland working on health inequalities today and the nature of Scotland's implementation gap when it comes to tackling them.
There was a clear degree of frustration from stakeholders that more sustainable change at scale has not been achieved over the last 20 years. While expressed in different ways, a consistent theme was that Scotland does not currently have the right balance of power or scale of investment in terms of driving meaningful action on health inequalities. This was felt at both a national and regional level and we repeatedly heard that Scotland can often feel overly centralised on these issues. This fed into the recurring concern around a lack of meaningful community empowerment across the country, despite many high profile initiatives in this space.
Another prominent theme from this work was around the implementation gap and a lack of long-term and cross-departmental thinking on policy making, resourcing and financing to reduce health inequalities. We heard that organisations face multiple competing demands and too many initiatives or services exist in isolation and receive only short-term or annualised funding. We also heard that Scotland lacks enough genuinely independent voices in this space that are not beholden to local or national government to constructively analyse and critique decision making.
With these points in mind, stakeholders expressed a clear desire for the Health Foundation's review of health inequalities to embrace its independence and take the opportunity to make a bold rallying call to renew cross-sector and cross-departmental efforts to address these issues.
As Scotland moves into a challenging period for our public finances and as individuals, families and communities across the country face some of the most difficult economic circumstances in a generation, the need to act in a more ambitious and coherent way to tackle health inequalities in Scotland has never been greater. Despite the challenges that exist, it has been inspiring to hear the passion and commitment from stakeholders across Scotland to tackling health inequalities. There is a broad and passionate coalition of the willing for an ambitious agenda in this space. The Health Foundation's independent review is the perfect catalyst to help Scotland to take bold steps; to think, plan and invest in the long-term preventative action needed to tackle health inequalities.
- For more information on the qualitative stakeholder engagement work, workshops and interviews undertaken by Nesta Scotland to inform this report, please contact: [email protected]
- For further information on the quantitative stakeholder survey undertaken by Diffley Partnership, including details of the type and geographical spread of respondents, please contact: [email protected]
The Nesta Scotland team wish to reiterate our thanks to all those individuals and organisations that generously gave of their time, wisdom and experience to contribute to this report.
The Bayes Centre
47 Potterrow
Edinburgh EH8 9BT
[email protected]
@nesta_scotland
nesta.uk
www.nesta.org.uk
Nesta is a registered charity in England and Wales with company number 7706036 and charity number 1144091. Registered as a charity in Scotland number SCO42833. Registered office: 58 Victoria Embankment, London EC4Y 0DS.
License: CC BY NC SA



